
What does a medical marketing agency do — and which kind are you talking to?
A medical marketing agency helps a physician-led practice win and keep patients: being found on Google and in AI answers, explaining treatments clearly, handling inquiries, and proving what the work returned. That description fits hundreds of medical marketing companies, which is exactly why it is not enough. Underneath the shared label sit five business models that behave very differently once the contract is signed.
| Agency type | What you usually get | How it is paid | Where it tends to break |
|---|---|---|---|
| Full-service healthcare agency | Website, SEO, paid ads, social, reporting under one account manager | Monthly retainer, ad spend on top | Breadth over depth; the invoice is the same in a quiet month |
| Specialty-only agency | Templates and playbooks for one field (dental, plastic surgery, med spa) | Retainer, sometimes a setup fee | The same template sold to your competitor across town |
| Single-channel specialist | Deep work on one channel: SEO, PPC, or social | Retainer or percentage of ad spend | Nobody owns the patient journey between channels |
| Pay-per-lead vendor | Form fills and calls delivered to the front desk | A price per lead | No-show leads and existing patients counted as new |
| Performance partner | Compounding content assets plus inquiry handling | A share of collected revenue in agreed lines | Only works if attribution is read from your own records |
None of these is wrong for every practice. A large hospital group with an in-house team may only need a single-channel specialist; a two-physician clinic may get more from one operator who carries the whole journey. The useful question is not “which agency is strongest” but which model's incentives match what you need: activity, leads, or revenue. Medical digital marketing services that never mention collected revenue are, by design, selling the first two.
Which contract model fits a medical practice?
Five contract shapes cover nearly every proposal you will see. A retainer buys a team's time each month, results or not. A project fee buys a deliverable — a new site, a content library — and ends at handover. Retainer plus ad spend adds media you fund directly, often with management fees on top. Pay-per-lead prices each contact, which sounds fair until you audit what counted as a lead. A revenue share ties the fee to income that actually lands, which only works when the agency accepts your system as the referee.
Published guides put general healthcare marketing retainers at $2,500–10,000 a month, rising to $8,000–20,000+ in competitive aesthetic fields, with ad spend billed separately. The full rate card lives on healthcare marketing agency cost; how to leave a retainer without a visibility gap is covered in no-retainer marketing agency; and the legal shape of a percentage fee is examined in performance-based healthcare marketing. This page stays on choosing the type.
What rules does medical marketing have to follow in the US, UK, and Australia?
A medical marketing firm writes words that patients read as your clinical voice, so its output inherits your obligations. In all three markets the regulator holds the clinician or practice responsible for what is published; delegating the writing does not delegate the accountability. A capable agency builds to those rules from the first draft rather than asking you to catch problems at sign-off.
US — FTC, HIPAA, and state fee laws
- FTC Endorsement Guides (2023 revision): a featured result is read as what patients can typically expect, and a “results not typical” line does not fix a misleading claim
- The FTC also holds agencies liable for deceptive content they knew, or should have known, was misleading
- HIPAA: patient stories, photos, and review replies that reveal who was treated need the patient's written authorization; tracking tools on pages that collect health details deserve a compliance check
- Federal fraud-and-abuse rules reach federal-program business; several states (CA, FL, NY) apply fee-splitting and patient-brokering limits to all payers
UK — GMC and ASA/CAP
- The GMC places responsibility for advertising on the doctor personally; it cannot be handed to an agency
- ASA/CAP expects testimonials to be genuine and representative, with no promised outcomes
- Cosmetic interventions carry extra limits: no time-limited offers, nothing that trivializes treatment, nothing aimed at under-18s
- CQC regulates the service itself rather than the marketing contract, but claims about the service still need to be accurate
Australia — AHPRA
- Testimonials about clinical aspects of care cannot be used in advertising, and sharing or linking to them counts too
- Guidelines for cosmetic procedures in force from 2 September 2025 add rules for higher-risk non-surgical treatments and bar advertising to under-18s
- Penalties reach AUD 60,000 for individuals and AUD 120,000 for bodies corporate
- Our Australian pages are AHPRA-compliant by construction: no testimonials, no outcome claims
One practical consequence: the contract with your agency should be as reviewable as the marketing. Our fee covers cash-pay and self-pay services only, leaves federal-program business out of scope, and offers a flat-tier alternative in states with stricter statutes. Ask your healthcare attorney to read it before you sign — we would rather you did. Australian practices will find the copy rules in detail on AHPRA-compliant clinic marketing.
What should a medical practice fix first at its size?
The right first project depends less on specialty than on how many physicians, locations, and decision-makers the practice has. Medical practice marketing that starts in the wrong place spends months polishing a layer the patient never reaches.
| Practice size | Fix first | Then | Usually premature |
|---|---|---|---|
| Solo physician or single location | Business Profile accuracy, one strong page per core service, an inquiry path that answers out of hours | A check of what AI engines say when asked about your services in your town | Brand campaigns, broad social ads |
| Multi-physician practice | A profile page per physician, service pages that name who performs each treatment, consistent practice details everywhere | Patient-language lines for the communities around you | Separate agencies per channel |
| Multi-location group | Location pages with genuinely local detail, one approval workflow, attribution from a single CRM | Central reporting across locations and engines | Copy-pasted city pages |
Across all three, the constant is ownership: the domain, the listings, the analytics property, and every account that holds patient-facing data should sit in the practice's name from day one. An agency should hold access, not title.
Which patients should medical practice marketing reach first?
Local patients first, every time. For most US, UK, and Australian practices, the people searching and asking AI about a treatment live within driving distance, and that domestic demand is the base the business stands on. Medical marketing for doctors that neglects the local base in favor of international ambitions tends to produce neither.
The upside runs through the same assets. Around 68 million Latinos live in the US, Sydney and Melbourne have large Chinese-speaking communities, and London treats more than 100,000 overseas patients a year. Pages that exist natively in those languages are found by people a monolingual competitor never reaches — including patients researching from abroad. How each language line works is set out in multilingual patient acquisition.
How do you vet medical marketing companies before you sign?
Ask questions that expose the operating model rather than the pitch. Who writes the clinical content, and who checks it against our market's rules? A named process beats a promise of “compliance.” Whose name are the domain, listings, ad accounts, and analytics registered in? The answer should be yours. Where does the revenue number in your report come from? If it is the agency's own tracking, you are grading their homework with their pen.
What happens to the pages if we leave? Which work do you subcontract, and to whom? And the most revealing one: what would you advise us not to buy? An agency that can name services you do not need yet is selling judgment, not hours. Medical marketing services that cannot answer these in writing are not ready to carry your name.
What proof is worth asking a medical marketing agency for?
Instruments, not adjectives. We show the screens we run every day: Google positions on 2,050 tracked keywords and citation checks across four AI engines. Our record was built in Seoul, the most crowded medical-tourism market we know of, where two dermatology clinics grew foreign-patient revenue in the language lines we ran by +200% and +186%.1
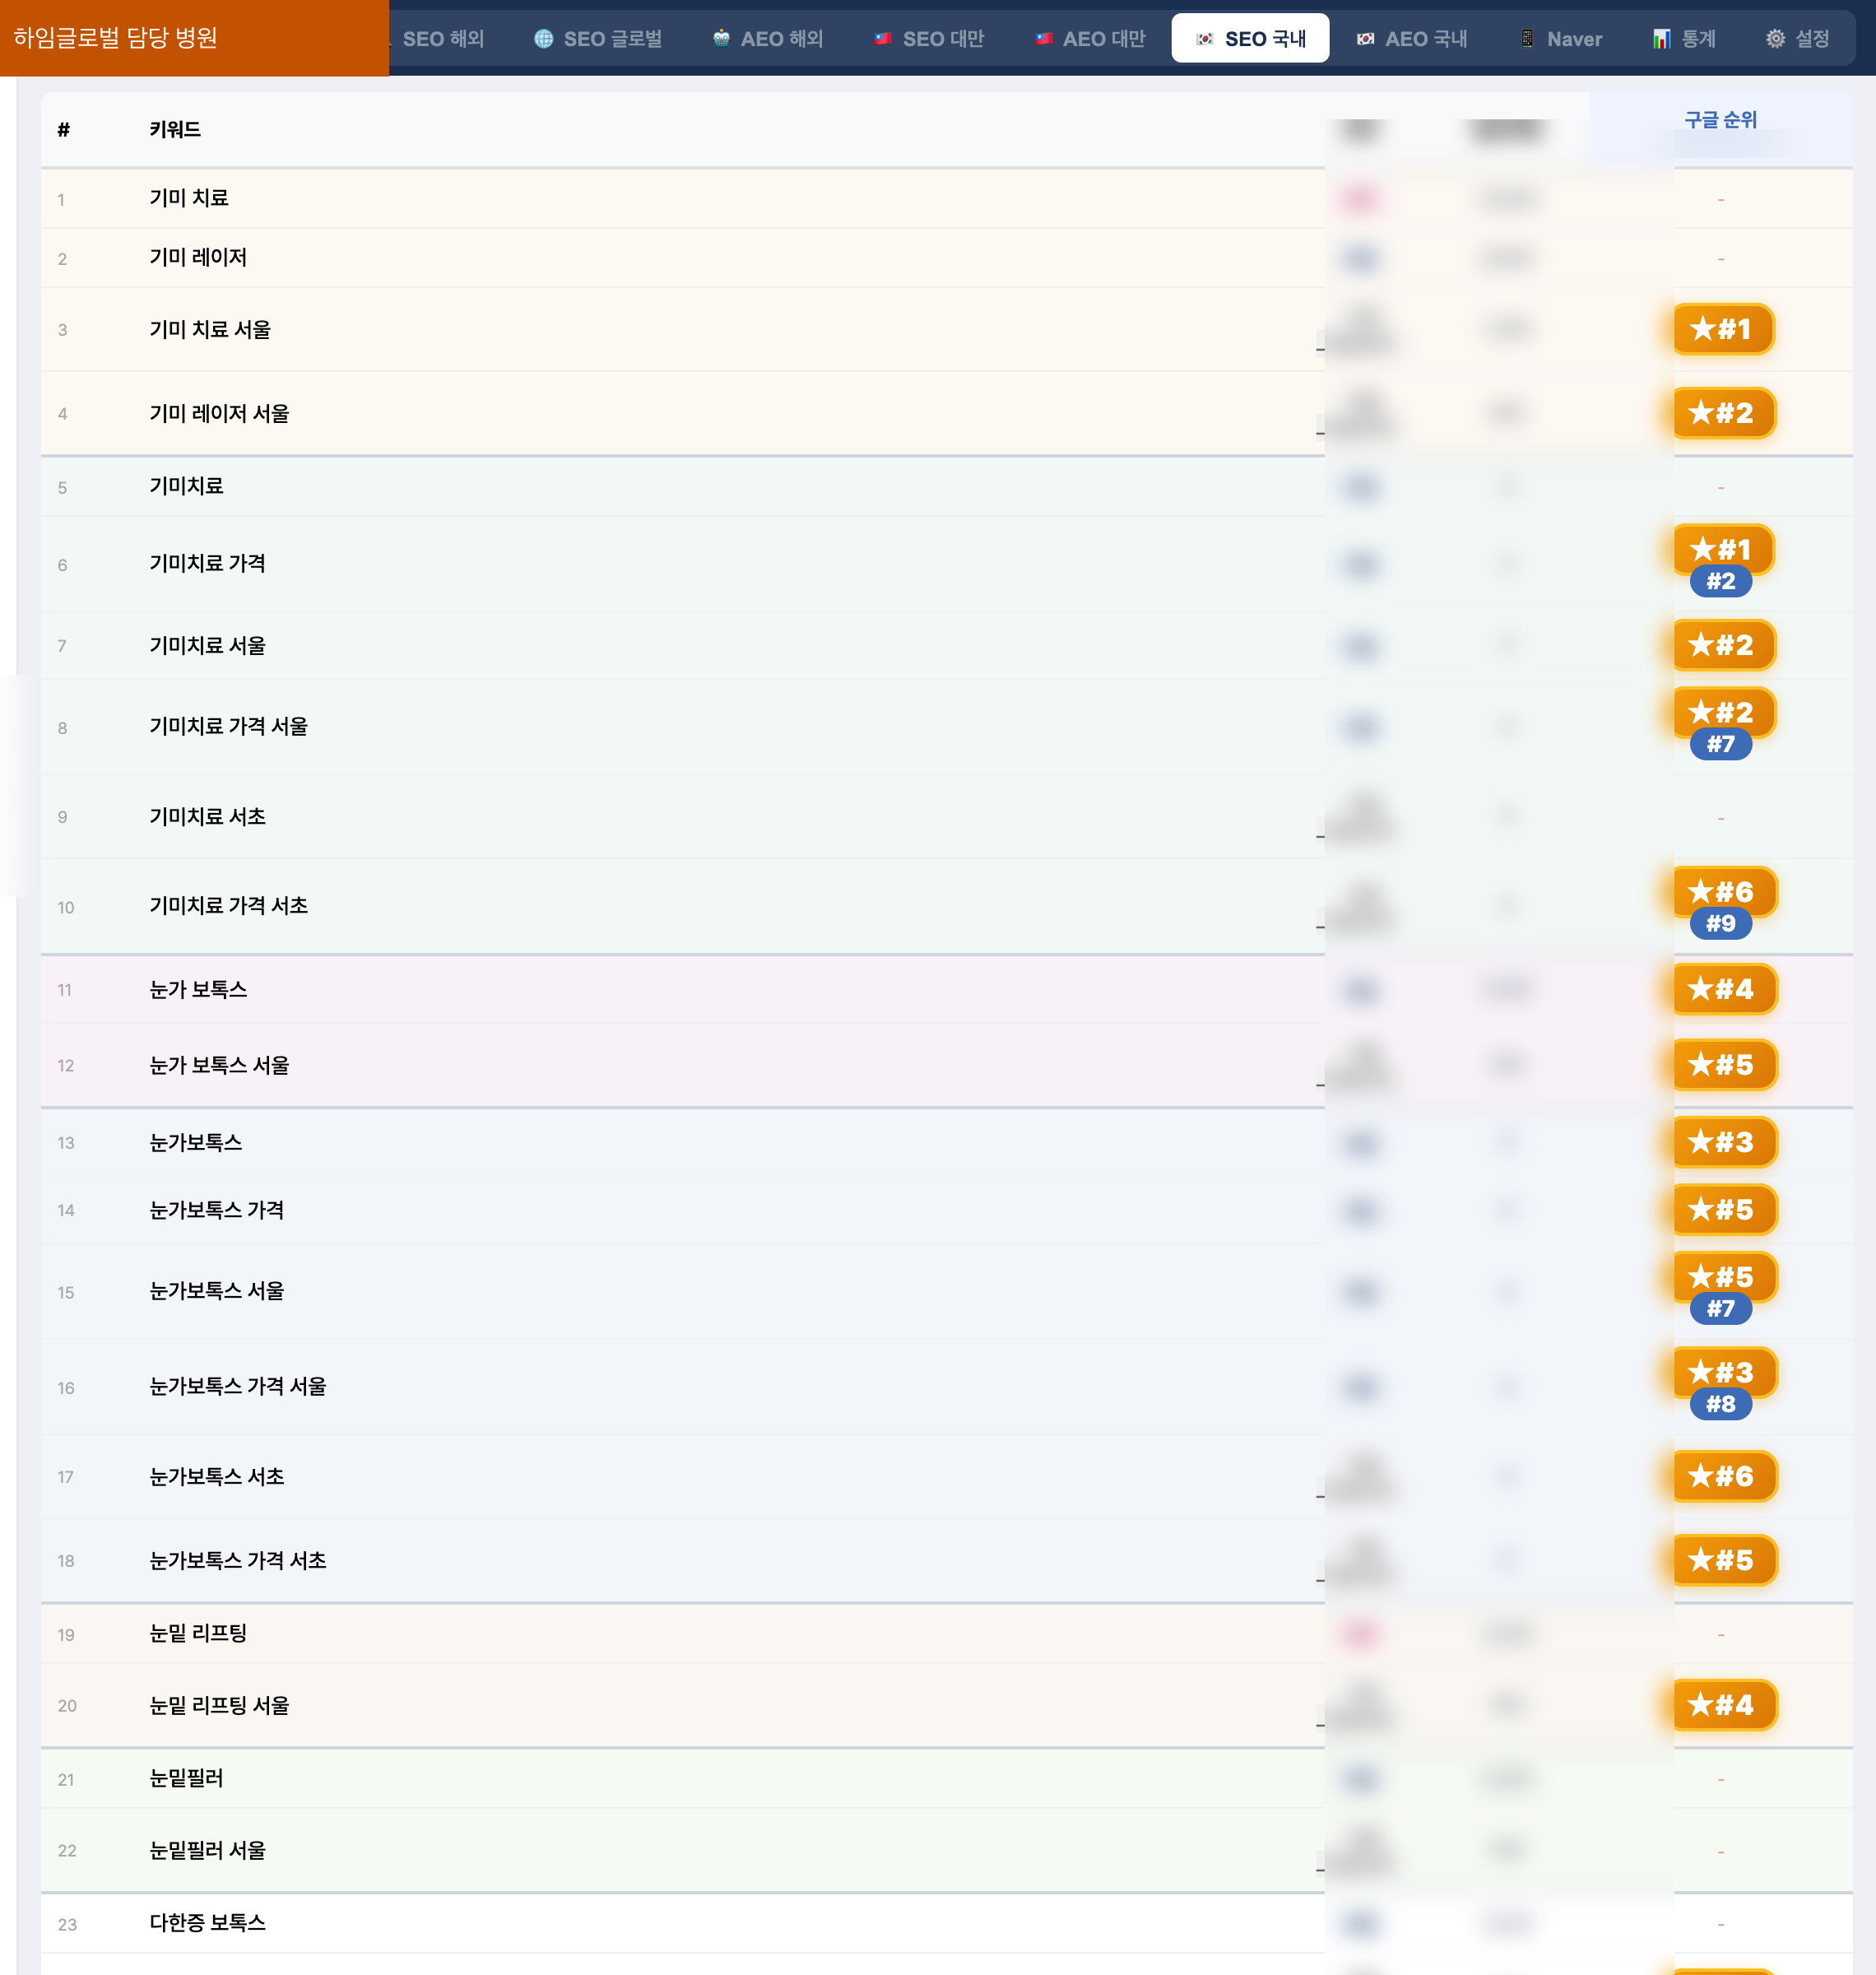
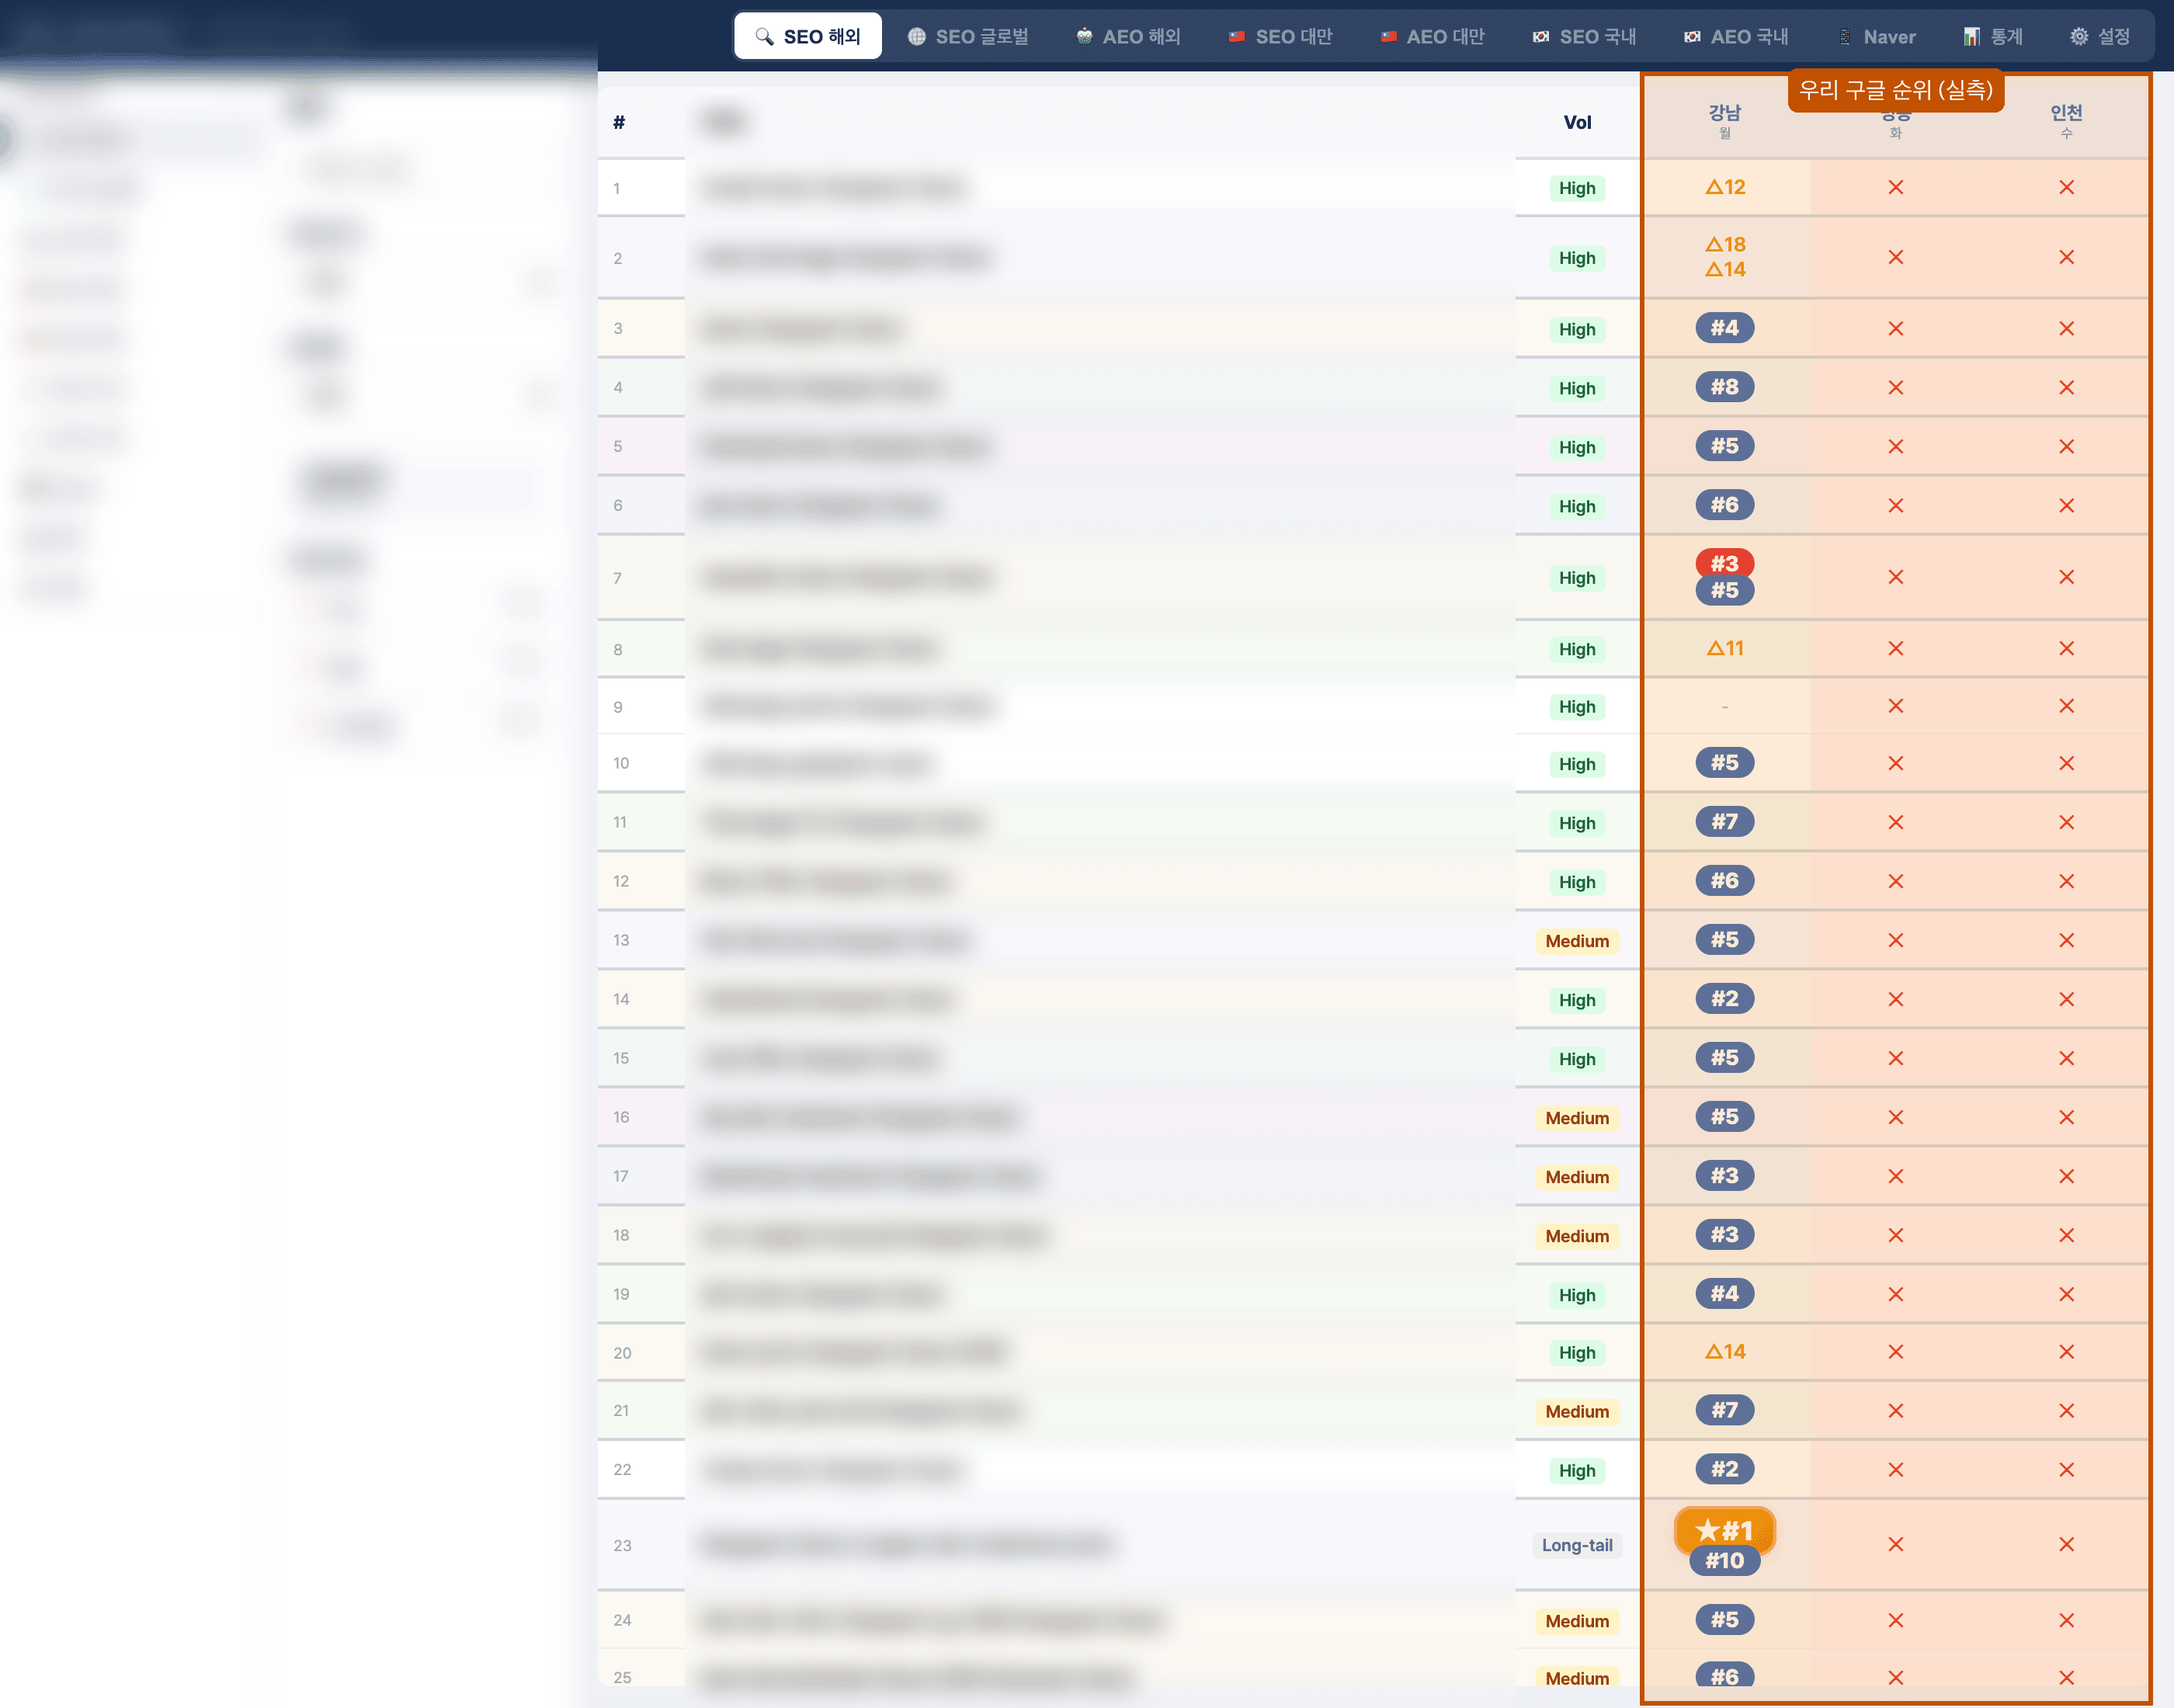
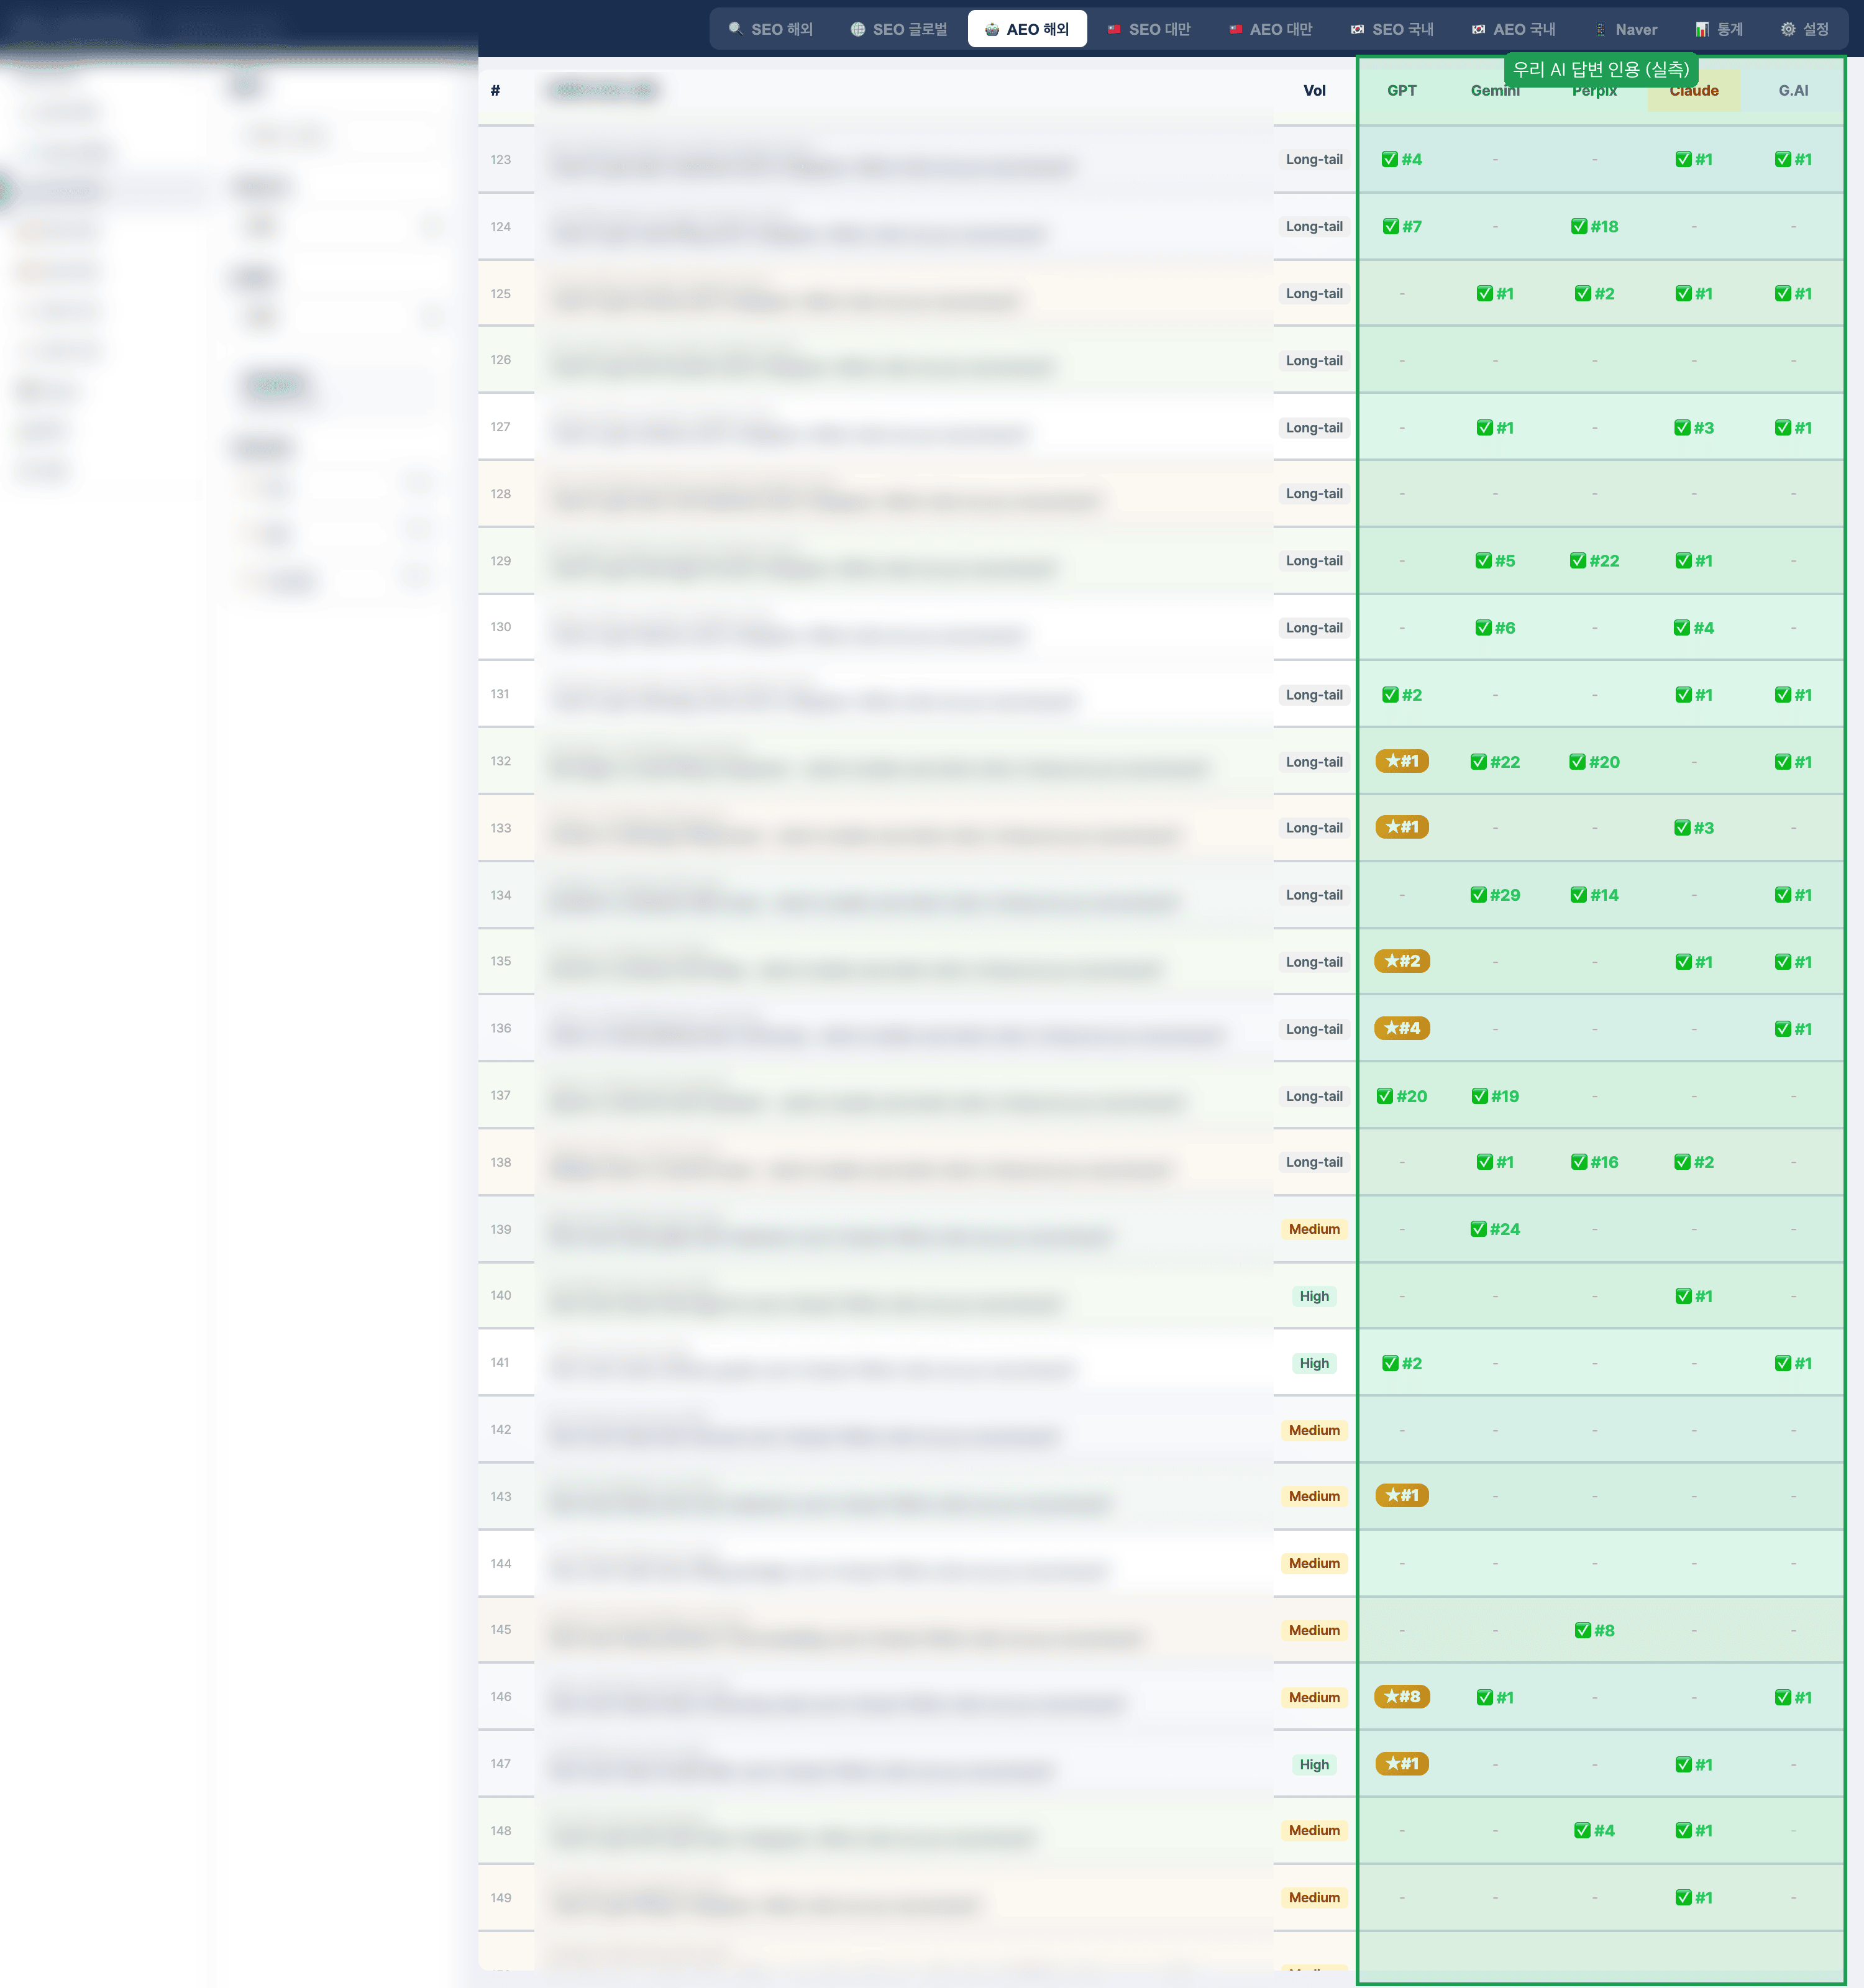
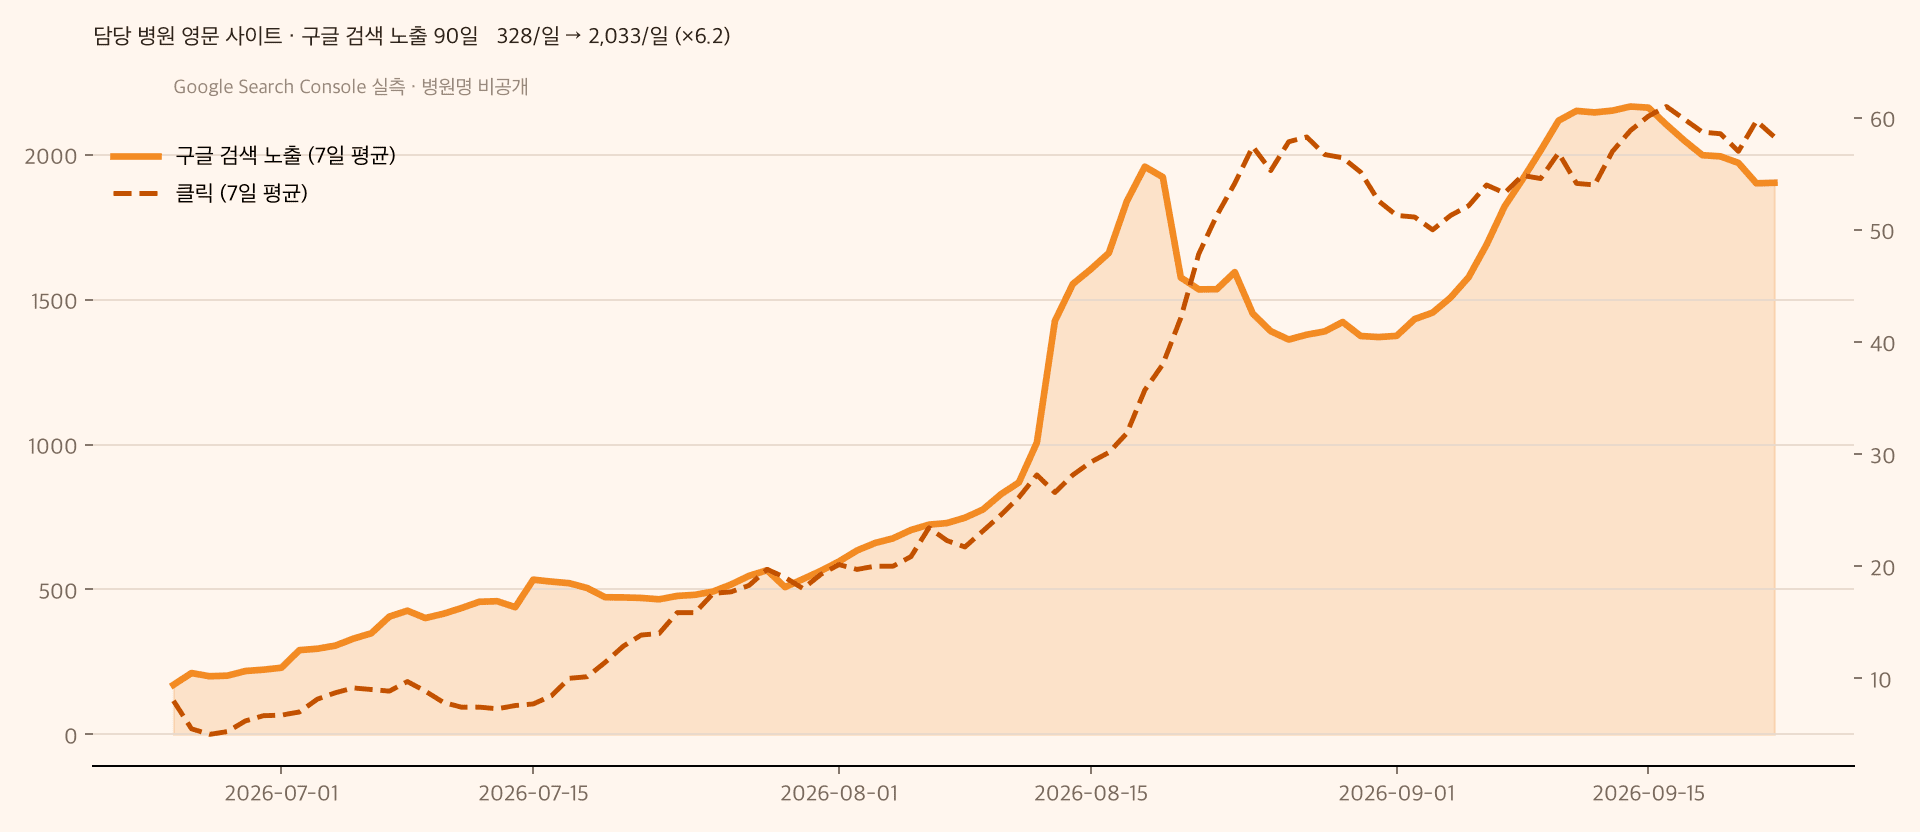
1 Source: internal CRM records of two Seoul dermatology clinics — foreign-patient revenue in the language lines assigned to us, against each clinic's prior baseline. Individual results vary by specialty, location, and competition. Names withheld under NDA; we walk through the live dashboards on the call.
How does HEIM GLOBAL work as a medical marketing agency?
As a performance partner, with the trade-offs that implies. $0 upfront — our fee is 30% of collected revenue from the patient lines you assign to us, CRM-verified, with no per-patient counting. We fund the content, hosting, tracking, and the 24/7 multilingual inquiry line; the base is designed around your practice during the free audit, normally excluding existing patients and channels you already run. Three terms come with it: $0 upfront · non-exclusive · monthly CRM settlement.
Where we are a poor fit, we say so. A practice whose revenue is mostly insurance or federal-program billing sits outside the fee's scope. A clinic that wants a weekly social calendar and billboard creative needs a different agency. And if your market has little room left, the free audit will show it before anything is signed. The full model, proof, and pricing are on the HEIM GLOBAL overview.
'/%3E%3C/svg%3E)